

Yes, most medicines can be safely rescheduled during Ramadan, but the answer depends on the route of administration. Oral tablets and nutritive drips generally break the fast, while injections, patches, inhalers, and eye or ear drops usually don't. Most people on regular medication can shift dosing to iftar and suhoor with a clinician's input, though some conditions, particularly unstable diabetes, make fasting genuinely risky. Speak to your prescriber or pharmacist before changing anything, and always treat medical emergencies as taking priority over the fast.
TL;DR:
- Injections, patches, inhalers, and eye or ear drops generally do not break the fast, unlike oral tablets, syrups, or nutritive feeding which do.
- Patients on fixed-dose or unstable conditions should seek professional guidance and consider rescheduling medications to promote safety during Ramadan.
- Long-acting formulations can simplify medication routines but require careful monitoring to avoid destabilizing well-controlled conditions.
- Dehydration from fasting can affect how certain drugs, especially diuretics and NSAIDs, are processed, so hydration management is crucial.
- Those with unstable health conditions or high-risk diseases like uncontrolled diabetes or recurrent hypoglycemia should consult their healthcare providers about whether fasting is safe at all.
Table of Contents
- Do you need a medication review before Ramadan?
- Which medication routes break the fast?
- How do you reschedule once, twice or three times daily doses?
- Which health conditions need extra caution during Ramadan?
- What should you ask your clinician or pharmacist?
- Are long-acting formulations a good alternative?
- Does fasting change how your medicines behave in your body?
- When is it better not to fast at all?
- Why most Ramadan medication advice misses the point
- Keep your Ramadan medication schedule on track
- Sources
Do you need a medication review before Ramadan?
Not everyone needs a formal appointment before the month begins, but a surprising number of people who should get one never do. Pharmacists at Australian Pharmacist have noted that many patients only mention their fasting plans if directly asked, meaning risky self-adjustments often go unnoticed until something goes wrong.
Run through this before deciding whether you need professional input:
- Is your condition currently stable, or have you had a dose change, hospital admission, or flare in the last three months?
- How many times a day do you take medication, and are any of them at fixed, non-negotiable times (insulin, anti-epileptics, blood thinners)?
- Do you take anything by injection, patch, inhaler, or drops that might not need rescheduling at all?
- Can you realistically fit two meals, hydration, and dosing windows into the hours between iftar and suhoor?
If you tick "unstable," "fixed timing," or "not sure" on any of those, book a review. Here's a simple order of operations:
- List every medicine you take, including over-the-counter products and supplements.
- Mark which ones are oral versus non-oral.
- Book a pharmacist or GP appointment four to six weeks before Ramadan, not the week before.
- Ask specifically about hydration needs alongside any dosing changes.
Pro Tip: Bring your medication list to the appointment sorted by time of day, not alphabetically. It makes the rescheduling conversation about five minutes shorter, because your pharmacist can see the clash points immediately.
Which medication routes break the fast?
This is the question most people get wrong, and it's worth being precise about it because the consequences of guessing badly range from an invalid fast to a genuine health risk.
Routes generally considered to break the fast:
- Oral tablets, capsules, liquids, and syrups
- Nutritive enteral feeding (tube feeds that deliver calories)
- Nutritive rectal preparations
Routes generally considered not to break the fast:
- Subcutaneous and intramuscular injections, including insulin
- Topical creams, gels, and transdermal patches
- Eye drops, ear drops, and ear or nasal sprays used for local effect
NHS-aligned guidance from CNWL sets out this same split, and Mayo Clinic's guidance reaches an almost identical conclusion independently, which tells you this isn't a fringe interpretation.
Inhalers and nasal sprays sit in genuinely contested territory. Some scholars class them as non-breaking because nothing nutritive reaches the stomach; others disagree because a small amount of the dose is unavoidably swallowed. If you rely on a preventer inhaler, don't guess your way through this one. Ask both your respiratory team and a religious authority you trust, and don't be surprised if the answer is "it depends on the school of thought you follow."
How do you reschedule once, twice or three times daily doses?
The mechanics here are genuinely different depending on how often you dose, so treat each pattern on its own terms rather than applying one rule to everything.
Once-daily medicines are usually the easiest to manage. The main decision is whether the drug needs food to reduce side effects (many statins, some antidepressants) or works best on an empty stomach (levothyroxine, for instance, is typically taken well before food). If food timing matters, your clinician will usually recommend either iftar or suhoor depending on which meal fits that requirement. If timing is flexible, most people find iftar easier to remember consistently.
Twice-daily medicines are where the real planning happens. The goal is the widest safe interval you can manage between the two non-fasting windows. A common pattern looks like this:
| Dosing slot | Typical timing | Notes |
|---|---|---|
| First dose | With iftar (sunset) | Take with or after breaking the fast |
| Second dose | With suhoor (pre-dawn) | As close to the fasting start as tolerated |
That gap between iftar and suhoor is rarely the full twelve hours a "every 12 hours" instruction implies, particularly in summer months in higher latitudes. Your clinician needs to know your actual sunset-to-dawn window, not just the drug label instructions, because a shortened interval can matter for drugs with a narrow safety margin.
Three-times-daily medicines are the hardest to fit into two eating windows, and this is exactly where clinicians start discussing whether an extended-release version of the same drug exists. Peer-reviewed guidance published in PMC specifically recommends considering long-acting formulations or regimen simplification when a three-times-daily schedule can't reasonably be compressed into iftar and suhoor.
Short courses, antibiotics, short analgesic bursts, and similar, are usually simpler to handle. If a once-daily alternative exists for the same course, ask your pharmacist about it rather than trying to squeeze a three-times-daily antibiotic into two windows for ten days straight.
Pro Tip: Never self-adjust a narrow therapeutic index drug, warfarin, lithium, phenytoin, and similar, based on advice from a leaflet or a friend's experience. These are the medicines where a few hours' shift in timing can meaningfully change blood levels, and only your clinician can judge that safely for your specific dose.
Which health conditions need extra caution during Ramadan?
Some conditions carry real risk during fasting, and the level of caution needed varies sharply by diagnosis rather than by medication count.
Diabetes is the condition with the clearest evidence base behind it. Fasting raises the risk of hypoglycaemia and, in some cases, diabetic ketoacidosis, and clinical reviews in PMC note that individualised education and glucose monitoring, including continuous glucose monitors where available, allow many patients to fast safely while others should not fast at all. Insulin doses very often need adjusting, not just retiming, and this decision belongs entirely with your diabetes team.
Epilepsy management depends on keeping steady drug levels in the blood. A shift in dosing times that creates an unusually long gap between doses can lower that level enough to provoke a seizure, so anyone on anti-epileptic medication should get specialist sign-off before changing their schedule, not just general advice from a pharmacist unfamiliar with their history.
Cardiovascular and kidney conditions raise dehydration as the central concern. Diuretics, in particular, need careful thought: taking a full dose at suhoor and then fasting through a hot day can push someone into significant fluid loss. Blood pressure and renal function are worth monitoring more closely during the month if you're on these drugs.
Mental health conditions carry one very specific warning: never stop a psychotropic medication abruptly to make fasting "easier." Sudden discontinuation of antidepressants or antipsychotics can trigger withdrawal effects or relapse, and rescheduling the dosing time is almost always safer than skipping doses.
Asthma management usually separates into two categories. Preventer inhalers generally continue on their normal (non-breaking) schedule, but anyone needing their reliever inhaler more than expected during fasting hours should treat that as a sign to seek urgent advice, not push through it for the sake of the fast.

What should you ask your clinician or pharmacist?
A good pre-Ramadan appointment is short if you come prepared. Bring three things: your current medication list with times, any monitoring logs you keep (blood glucose readings are the most common), and recent results from blood tests if you've had any in the last few months.
Ask these questions directly:
- Can any of my doses shift to iftar or suhoor without losing effectiveness?
- Is there a once-daily or extended-release version of this medicine that would fit better?
- What symptoms should make me stop fasting and seek help immediately?
- Do I need any extra monitoring, blood pressure, glucose, kidney function, during the month?
- What's the safest way to catch up if I accidentally miss a dose?
Watch for red flags in the conversation. If your clinician hesitates, mentions recent instability, or brings up a recent hospital admission, that's usually a sign fasting isn't advisable this year, even if you fasted safely in previous ones. Pharmacists are often the most practical resource here: Islamic Relief's guidance points out that many patients simply skip or alter doses on their own because nobody asked them about their fasting plans, so raise it yourself if your pharmacist doesn't.
Pro Tip: If you're managing several conditions at once, ask your pharmacist to map your entire day, medicines, meals, and sleep, on a single sheet rather than discussing each drug separately. Interactions between your rescheduled doses often only become obvious when you see the whole day laid out together.
Are long-acting formulations a good alternative?
Sometimes, but not automatically. Extended-release tablets, once-daily patches, and depot injections given every few weeks can genuinely simplify a complicated day, turning a three-times-daily headache into something that fits neatly around iftar.
The trade-off is real, though. Switching formulations changes how a drug is absorbed and released, and a regimen that's been stable for years can behave differently on a new preparation. One clinical insight worth taking seriously: switching to a long-acting version purely to make Ramadan easier can destabilise a previously well-controlled condition if it isn't monitored closely afterwards.
That means:
- Formulation swaps should only happen with a clear clinical reason and follow-up plan, not as a convenience shortcut arranged the week before Ramadan.
- Depot injections and patches suit drugs where steady blood levels matter more than exact timing, insulin patches and certain hormonal treatments are common examples.
- Anyone switching formulations should have a check-in scheduled during the month, not just before it, to confirm the new version is working as expected.
Does fasting change how your medicines behave in your body?
Fasting doesn't just change when you take a tablet. It changes hydration levels, and hydration affects how your kidneys clear certain drugs from your bloodstream. Reduced fluid intake during daylight hours can concentrate drugs that rely on renal clearance, and this is exactly why NSAIDs and diuretics carry elevated risk during Ramadan.
Practical steps that help:
- Spread fluid intake across the non-fasting hours rather than drinking most of it at once during iftar.
- Avoid or minimise NSAID painkillers during fasting hours if you're already on a diuretic or have reduced kidney function.
- Ask your clinician whether renal function or electrolyte tests are worth checking partway through the month, particularly if you're on multiple medicines that affect fluid balance.
Clinical guidance in PMC makes the hydration point explicitly: dehydration during fasting hours can alter drug concentrations enough to matter clinically, not just theoretically, which is why this gets flagged so consistently in condition-specific advice.
When is it better not to fast at all?
Some situations call for skipping the fast rather than trying to engineer around it. These include unstable or poorly controlled chronic disease, recurrent severe hypoglycaemia, and pregnancy where fasting poses a clear risk to mother or baby.
Islamic teaching is unambiguous that health takes priority here. Guidance summarised by the ETHNOMED bulletin confirms that someone whose health would be endangered by fasting is permitted to delay their fast and make up the missed days later, or offer fidya (feeding someone in need) where making up days isn't possible. If you're uncertain which applies to your situation, a scholar you trust can guide you alongside your clinician, and the two conversations aren't in conflict.
If you're advised not to fast this year, the practical next step is simple: confirm the plan with your clinician in writing if possible, and discuss the make-up or fidya route with someone qualified to advise on it.
Why most Ramadan medication advice misses the point
The conventional advice on this topic tends to focus entirely on timing tables, move this dose here, that one there, and almost completely ignores the fact that most medication errors during Ramadan happen because nobody had the conversation at all. Pharmacists consistently report that patients quietly stop or shuffle doses without telling anyone, which is a far bigger risk than any specific timing choice.
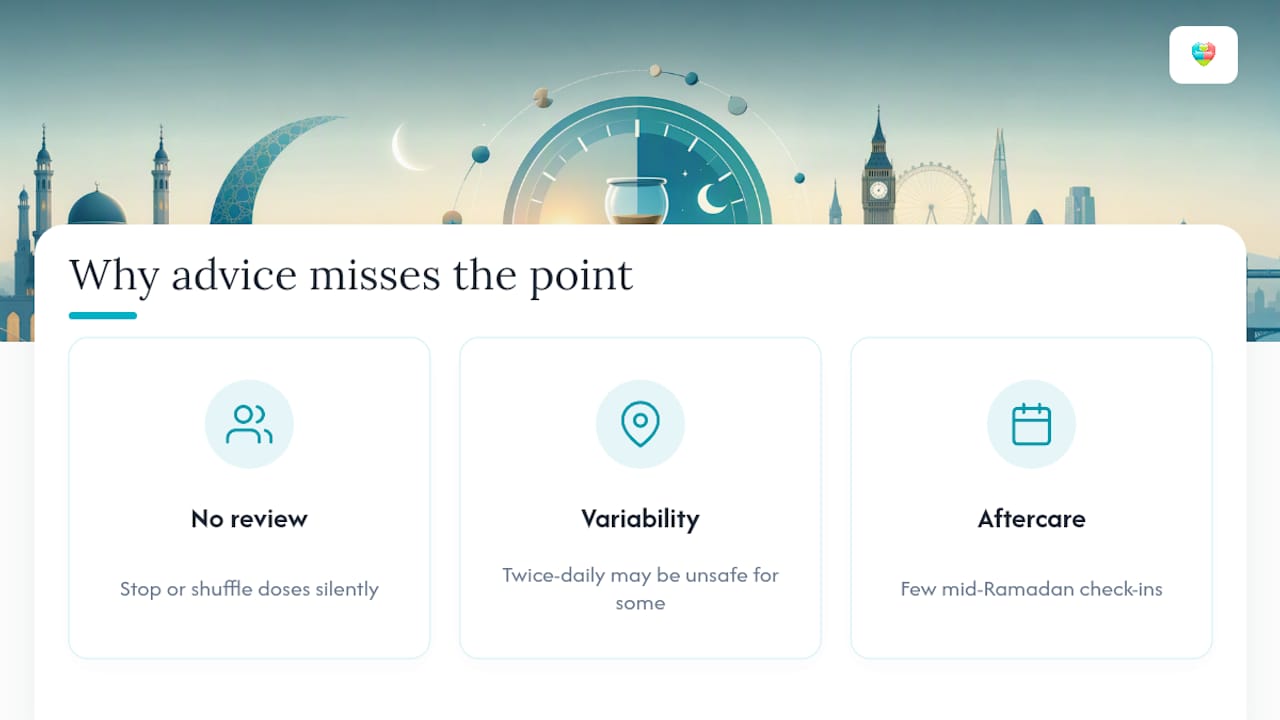
What gets underestimated is how much this varies person to person. A twice-daily regimen that works perfectly for one person's sunset-to-dawn window can be genuinely unsafe for someone else living further north with a much shorter non-fasting period. Generic timing charts can't account for that, and treating them as gospel is where a lot of well-intentioned self-management goes wrong.
The other gap is aftercare. Everyone talks about the pre-Ramadan review, far fewer talk about checking in partway through the month once the new routine has actually been tested against real life, missed meals, unpredictable iftar timings, travel. A schedule that looked sound on paper in early March can quietly drift by the third week.
— Prasant
Keep your Ramadan medication schedule on track
Rescheduling doses around iftar and suhoor is easier to plan than to remember consistently, especially across a household where several people are adjusting their routines at once. Thedailydosetracker gives you a practical way to hold that plan together once your clinician has agreed it, with custom schedules built around your actual dosing windows rather than generic once/twice/three-times-daily defaults.
You can log doses as they're taken, set real-time alerts for anything due, and flag drug interactions before they become a problem, all from one shared view if you're coordinating medication for a parent or family member during the month. The medication schedule organisation tools work well alongside the kind of clinician-approved timing changes discussed here, and you can export your history to share directly with a pharmacist or GP at your mid-Ramadan check-in. Try the free tier at Thedailydosetracker and set up your Ramadan schedule before the month starts.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Managing medications during Ramadan fasting - PMC
- Taking medication during Ramadan | CNWL NHS
- Ramadan and taking medication | Islamic Relief
- Health provider guidance for Ramadan (ETHNOMED bulletin) 2025
- Managing your health during Ramadan fasting - Mayo Clinic News Network